Knee arthritis can make routine activities surprisingly difficult. Climbing stairs, walking through a grocery store, getting out of a car, or sleeping comfortably may become harder over time. But a painful knee does not automatically need replacing. A discussion about total knee replacement becomes useful when symptoms and loss of function remain substantial despite reasonable nonsurgical treatment, and an examination shows that the joint damage and your goals make surgery worth considering. [1, 2]
What a total knee replacement changes
The knee has cartilage-covered surfaces at the lower end of the thighbone (femur), upper end of the shinbone (tibia), and behind the kneecap (patella). Osteoarthritis can damage those surfaces and the surrounding joint structures, causing pain, stiffness, swelling, and difficulty moving. Pain alone does not reveal how many areas of the knee are affected. [2]
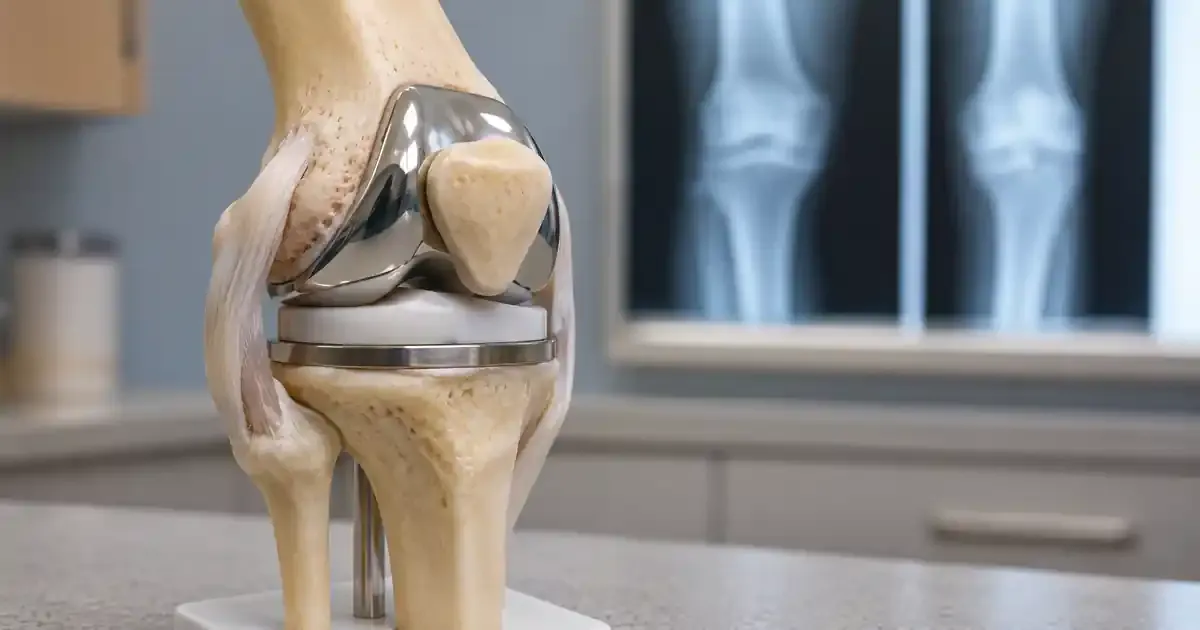
In a total knee replacement, the surgeon removes the damaged joint surfaces and fits artificial components, typically metal surfaces separated by a durable plastic bearing. The kneecap surface may also be treated when appropriate. The purpose is to address pain and functional limitations related to advanced joint disease. It is not a cure for every type of leg pain, and it cannot guarantee that the knee will feel or move exactly like a natural joint. [1]
Total replacement is different from a partial knee replacement, which addresses arthritis mainly confined to one compartment. The pattern of disease, knee alignment, ligament function, and other findings help determine which options may fit. An evaluation is needed before deciding whether either procedure makes sense.
When is it time to discuss surgery?
A surgical conversation may be appropriate if pain is persistent or worsening, walking distance is shrinking, or sleep, work, and daily activities are affected despite a thoughtful treatment plan. Some people notice that they plan their day around avoiding stairs, standing, or outings. Others find that they can no longer participate in activities important to them. These experiences matter because treatment decisions should reflect both symptoms and function, not an X-ray alone. [1, 2]
There is no universal age, pain score, or waiting period that makes replacement mandatory. A person with severe-looking X-rays may be coping reasonably well and prefer nonsurgical care. Another person may have significant limitations that deserve a careful discussion. A consultation does not commit you to an operation; it helps clarify why surgery is or is not being considered.
For people who already have symptomatic moderate-to-severe arthritis confirmed on imaging, have tried appropriate nonsurgical care, and have jointly decided that replacement is indicated, the 2023 American College of Rheumatology and American Association of Hip and Knee Surgeons guideline conditionally advises against delaying surgery solely to repeat additional courses of physical therapy, medication, or injections. The evidence for these timing recommendations is low or very low certainty. They do not mean that all knee pain should be treated surgically or that medical readiness can be ignored. [3]
What treatment should be reviewed first?
Many people manage knee osteoarthritis through exercise, strengthening, guided physical therapy, pacing of painful activities, weight management when appropriate, and supports such as a cane or brace. Topical or oral medication may be an option after considering other health conditions and medication risks. Injections may sometimes offer temporary relief, but they are not interchangeable and do not rebuild widespread lost cartilage. [2, 4]
You can learn about the practice's arthritis and joint-pain care and the recent discussion of knee injection options. Bring a record of what you have tried, how long you tried it, and what improved or did not. No one should be forced into an unnecessary series of treatments simply to postpone an operation they and their surgeon have already determined is appropriate. At the same time, it is reasonable to choose continued nonsurgical treatment when symptoms are tolerable or surgery does not fit your preferences.
What happens during the evaluation?
A clinician will ask where pain occurs, how long it has been present, whether there was an injury, and which activities are hardest. The examination may assess motion, swelling, tenderness, alignment, walking pattern, strength, and ligament stability. It should also consider whether the problem might be coming from the hip, back, meniscus, tendons, or another source. New knee pain after an injury is evaluated differently from gradual arthritis symptoms. [1, 2]
Weight-bearing X-rays often help show loss of joint space, deformity, and arthritis affecting more than one part of the knee. Advanced imaging is not routinely required for straightforward osteoarthritis, although other tests may be useful when the diagnosis is uncertain. Wiki Wiki Orthopedics lists knee evaluations and on-site X-rays with advanced-imaging referrals. The actual plan depends on the examination and the question being investigated.
If surgery is discussed, ask which parts of the knee are damaged, what symptoms replacement is intended to improve, and what might remain afterward. A clear explanation should also include reasonable alternatives, the risks of surgery, and what happens if you prefer to wait.
Planning, robotics, and recovery
Planning a replacement involves assessing the anatomy, alignment, motion, and stability of the knee. The surgeon selects components and a surgical technique based on those findings. Some procedures use robotic assistance to help with planning or execution; others are performed with conventional instruments. Robotics is a tool, not a promise of a better result for every patient. Ask what technology is proposed, why it might help in your case, and what evidence supports its use. [1]
Recovery is more than the operation itself. Early walking, rehabilitation, swelling control, wound care, and exercises to improve motion and strength are important parts of the process. Some selected patients may leave a facility on the day of surgery, while others need more monitoring or support. The discharge plan depends on overall health, medical risks, mobility, available help at home, and the treating team. A specific recovery speed should never be guaranteed. [1]
Complications can include infection, blood clots, stiffness, nerve or blood vessel injury, persistent pain, and problems with the implant over time. A surgeon should discuss your individual risk factors and the steps planned to reduce them. Before scheduling, review medications, diabetes control, nicotine exposure, prior infections, other medical conditions, and any anticipated need for assistance at home. The 2023 guideline supports addressing important issues such as poorly controlled diabetes and nicotine use rather than applying an arbitrary waiting period to everyone. [3]
Wiki Wiki Orthopedics lists total knee replacement among its surgical services. Whether surgery, robotic assistance, or an outpatient pathway is appropriate for a particular person must be confirmed during a consultation.
When knee symptoms need faster care
Longstanding arthritis typically allows time for a scheduled visit. A sudden very hot, red, markedly swollen, and intensely painful knee—especially with fever or feeling ill—needs urgent assessment for possible infection. After a fall or injury, a visible deformity, inability to bear weight, or a cold, pale, or numb foot also warrants prompt emergency evaluation. Call 911 for a life-threatening emergency, collapse, or major injury.
For routine symptoms, bring prior imaging, medication information, details of previous treatment, and a short list of activities you would most like to regain. Asking whether a total replacement is appropriate is a request for an informed evaluation, not a decision to have surgery that day.
Sources
- Total Knee Replacement, American Academy of Orthopaedic Surgeons, OrthoInfo.
- Arthritis of the Knee, American Academy of Orthopaedic Surgeons, OrthoInfo.
- 2023 ACR/AAHKS Clinical Practice Guideline for the Optimal Timing of Elective Hip or Knee Arthroplasty, American College of Rheumatology and American Association of Hip and Knee Surgeons, 2023.
- Osteoarthritis: Diagnosis, Treatment, and Steps to Take, National Institute of Arthritis and Musculoskeletal and Skin Diseases.
For non-emergency knee symptoms on Oahu, request an appointment or call (808) 439-6201.